PTSD Treatment Options: Proven Therapies Compared

Several treatments work. The one that works for you depends on what you can actually tolerate doing.

Table of Contents

  1. PTSD Treatment Options at a Glance
  2. Trauma-Focused Therapies
  3. EMDR
  4. Medication for PTSD
  5. Where Ketamine Fits
  6. Choosing Between Them
  7. FAQs About PTSD Treatment Options
You have read that PTSD is treatable and found four different treatments with unfamiliar names, each described as effective. They are not interchangeable, and the differences matter more for what the process feels like than for whether they work. PTSD treatment options divide broadly into trauma-focused psychotherapies, medication, and newer approaches used where standard treatment has not helped. This guide covers what each involves in practice.

PTSD Treatment Options at a Glance

Treatment What it involves Typical length
Prolonged exposure Gradual approach to trauma memories and avoided situations Around 8 to 15 sessions
Cognitive processing therapy Examining and changing trauma-related beliefs Around 12 sessions
EMDR Recalling trauma when doing a bilateral task Varies, often 6 to 12 sessions
SSRIs and SNRIs Daily medication Ongoing, reviewed periodically
Prazosin Targets trauma-related nightmares in particular Ongoing
Ketamine Off-label, where standard treatment has not helped Course of sessions
Trauma-focused psychotherapies are usually recommended as first-line for PTSD by major guidelines, including those from the Department of Veterans Affairs and the American Psychological Association. Medication is effective and is usually positioned alongside or after therapy rather than instead of it.

Trauma-Focused Therapies

Two have particularly strong evidence and they work differently. Prolonged exposure. Involves gradually approaching trauma memories and avoided situations rather than continuing to avoid them. Avoidance maintains PTSD, and systematic approach reduces it. Sessions include structured recounting of the trauma memory and real-world practice between sessions. It is demanding. Symptoms sometimes increase temporarily before improving, which is why it is done with a trained therapist rather than attempted alone. Cognitive processing therapy. Focuses on the beliefs formed so of trauma, particularly around safety, trust, control, and self-blame. It involves written work and structured examination of those beliefs. It usually involves less direct recounting of the trauma than prolonged exposure, which some people find more tolerable. Both are time-limited, structured, and among the most researched psychological treatments in existence.

EMDR

Eye movement desensitization and reprocessing involves recalling elements of the trauma when performing a bilateral task, usually following the therapist’s hand movements with your eyes. It is recommended in several major treatment guidelines and has substantial evidence for PTSD. The mechanism is debated. Some researchers attribute the effect to the bilateral stimulation, others argue the active ingredients are the exposure and processing that occur alongside it. That debate concerns why it works rather than whether. Practically, many people find EMDR requires less detailed verbal description of the trauma than prolonged exposure, which matters for those who find recounting intolerable. Sessions typically involve preparation and stabilization work before any processing begins.

Medication for PTSD

Medication is effective and is usually used alongside therapy. SSRIs and SNRIs. Certain SSRIs carry FDA approval for PTSD, and both classes are commonly used. They take several weeks to reach effect and address the broader symptom picture including mood, anxiety, and hyperarousal. Prazosin. A blood pressure medication used off-label for trauma-related nightmares in particular. Evidence is mixed and it remains widely used for that symptom, which is often among the most distressing. Benzodiazepines. Usually not recommended for PTSD. Guidelines advise against them, since evidence does not support benefit and they may interfere with the processing that therapy depends on. Dependence risk applies as elsewhere. That last point runs against what some people are prescribed, and it is the current guideline position. Sleep problems, depression, and substance use frequently coexist with PTSD and each may need addressing alongside.

Where Ketamine Fits

Ketamine has been studied in PTSD, with some research reporting reductions in symptom severity. The evidence base is smaller than for depression, and effects in published work have often been temporary, raising unresolved questions about maintenance. Positioning matters. Ketamine is not a first-line PTSD treatment and does not replace trauma-focused therapy. Where it is used, it is usually for people who have not responded adequately to standard approaches, or where severe symptoms make engaging in therapy difficult. A reasonable framing is that reduced symptom severity may create a window in which trauma-focused therapy becomes possible for someone previously unable to tolerate it. The National Center for PTSD publishes treatment information and is the most substantial public resource on this condition.

Choosing Between Them

Several practical factors matter more than small differences in reported effectiveness. What you can tolerate. A highly effective treatment you cannot bring yourself to attend is less useful than a slightly less effective one you complete. If detailed recounting feels impossible, that points away from prolonged exposure. Your symptom pattern. Nightmares dominating the picture may point toward addressing that in particular alongside broader treatment. Coexisting conditions. Substance use, severe depression, or active suicidality usually need addressing alongside or first. Stability. Trauma-focused work requires a degree of stability. Where life circumstances are chaotic or unsafe, stabilization comes first. Availability. Trained therapists in specific modalities are not equally available everywhere. Complex PTSD from prolonged repeated trauma usually requires a phase-based approach with stabilization before processing, and longer treatment overall.

FAQs About PTSD Treatment Options

Which PTSD treatment works best? Trauma-focused psychotherapies including prolonged exposure, cognitive processing therapy, and EMDR have the strongest evidence and are recommended first-line by major guidelines. No single one is best for everyone. What you can tolerate attending and completing matters as much as reported effectiveness. Do I have to talk about the trauma in detail? It depends on the treatment. Prolonged exposure involves structured recounting. Cognitive processing therapy focuses more on beliefs than on detailed narration. EMDR typically requires less detailed verbal description. If recounting feels intolerable, say so, since it directly affects which treatment suits you. Does medication alone treat PTSD? Medication is effective and is usually positioned alongside therapy rather than instead of it. Certain SSRIs carry FDA approval for PTSD. Trauma-focused psychotherapy is recommended first-line, and combined treatment suits many people, particularly where depression or sleep problems coexist. Can PTSD be treated years after the trauma? Yes. Treatment is effective regardless of how long ago the trauma occurred, including decades later. Delay does not reduce the likelihood of benefit. Many people first seek treatment years afterward, often when something triggers a return of symptoms. Is ketamine used for PTSD? It has been studied with some research reporting reduced symptom severity, and the evidence base is smaller than for depression with effects often temporary in published work. It is not a first-line treatment and does not replace trauma-focused therapy. It is usually considered where standard approaches have not helped sufficiently.

Discuss Which Approach Fits

The right treatment depends on your symptoms, what else is going on, and what you can realistically engage with. That is an assessment rather than a choice from a list. Dr. Sambunaris & Associates treats PTSD in Alpharetta, Georgia. Book My Assessment or call (770) 817-9200. Reviewed by Angelo Sambunaris, M.D., with more than 20 years of clinical experience. If you are having thoughts of suicide or self-harm, call or text 988 to reach the Suicide and Crisis Lifeline, available 24 hours a day. This article is general information, not medical advice.  

Recent Posts

Psychiatrist vs Therapist: Avoid the Costly Mix-Up

Booking the wrong one wastes six weeks and a copay. The difference takes two minutes to understand.

Table of Contents

  1. Psychiatrist vs Therapist: The Short Answer
  2. What Each Professional Actually Does
  3. Who Can Prescribe Medication
  4. Which One Should You Book First?
  5. Working With Both at Once
  6. Cost and Insurance Differences
  7. FAQs About Psychiatrist vs Therapist
You have decided to get help. Now you are looking at a list of professionals with different letters after their names and no idea which one solves your problem. Booking the wrong one is common and costly. People spend months in talk therapy for a condition that needed medication, or start medication with nobody addressing what is driving the problem. Understanding psychiatrist vs therapist takes a couple of minutes and saves considerably longer. This guide covers what each does, who prescribes, and how to choose the right first appointment.

Psychiatrist vs Therapist: The Short Answer

A psychiatrist is a medical doctor who specializes in mental health and can prescribe medication, order tests, and diagnose conditions medically. A therapist provides talk therapy and usually cannot prescribe. A psychologist holds a doctorate in psychology, provides therapy and psychological testing, and in most states cannot prescribe. The simplest distinction is that psychiatrists treat medically, therapists and psychologists treat through structured conversation. Many people need both, working together. The titles overlap in daily speech, which is why the confusion persists. “Therapist” is used broadly and covers several different licenses.

What Each Professional Actually Does

Psychiatrist Psychologist Therapist / Counselor
Training Medical degree plus psychiatry residency Doctorate in psychology Master’s degree, varies by license
Prescribes Yes Rarely, only in some states No
Provides talk therapy Sometimes Yes Yes
Psychological testing Orders and interprets Administers and interprets Usually no
Medical investigation Yes, including bloodwork No No
Typical appointment Shorter, medication focused 50 minutes 50 minutes
“Therapist” covers several licenses, including licensed professional counselors, clinical social workers, and marriage and family therapists. Their training differs and all provide talk therapy. The practical difference that matters most is the medical one. A psychiatrist can investigate whether a thyroid problem, a medication interaction, or a sleep disorder is producing your symptoms. That is outside a therapist’s scope entirely.

Who Can Prescribe Medication

Prescribing authority is the clearest dividing line. Psychiatrists prescribe and manage psychiatric medication, including controlled substances such as stimulants for ADHD. Psychiatric nurse practitioners, often listed as PMHNP, prescribe in most states, sometimes independently and sometimes under physician collaboration depending on state law. Primary care physicians prescribe common psychiatric medications and manage many straightforward cases. Psychologists cannot prescribe in most states. A small number of states allow it with additional training. Therapists and counselors do not prescribe. Georgia does not grant prescribing authority to psychologists, so in this state the practical choice for medication is a psychiatrist, a psychiatric nurse practitioner, or your primary care physician.

Which One Should You Book First?

Match the first appointment to your situation rather than starting wherever there is an opening. Start with a psychiatrist if you want medication or need it reviewed, previous medication has not worked, symptoms are severe or affecting your ability to function, you suspect ADHD and need assessment and prescribing, or a physical cause needs excluding. Start with a therapist if you want to work through a specific situation such as grief, a relationship, or a life change, your symptoms are mild to moderate, or you would prefer to try therapy before medication. Start with a psychologist if you need formal psychological testing, or want therapy from someone with doctoral-level training in a specific modality. Start with your primary care physician if you are unsure where to begin and want a referral, or need physical causes ruled out first. One more consideration. Waiting lists for psychiatry are often longer than for therapy. If you think you will eventually need both, booking the psychiatric assessment early when starting therapy sooner is a reasonable sequence.

Working With Both at Once

Combined care is common and, for several conditions, better than either alone. Research across depression and anxiety consistently finds combined medication and psychotherapy outperforming either treatment individually for many people. The American Psychiatric Association publishes patient guidance on treatment approaches. How it works in practice. The psychiatrist manages diagnosis and medication, seeing you less frequently once stable. The therapist does the weekly work of changing patterns, processing events, and building skills. The two should communicate, with your consent. That coordination is what makes combined care work rather than two disconnected treatments running in parallel. Ask each professional whether they are willing to coordinate. Most are, and it takes a signed release.

Cost and Insurance Differences

Cost structures differ in ways worth knowing before booking. Psychiatric appointments are usually shorter than therapy sessions, with a longer initial evaluation followed by briefer medication management visits. Therapy is typically weekly or fortnightly at 50 minutes. Insurance commonly covers both, with different copay structures and sometimes different networks for mental health. Some psychiatrists do not participate in insurance networks, which affects cost substantially. Four questions to ask any practice before your first appointment.
  1. Do you take my insurance, and are you in network?
  2. What does the initial evaluation cost, and what do follow-ups cost?
  3. How long is the wait for a first appointment?
  4. Do you coordinate with an outside therapist?
Ask your insurer the same questions separately. Where the answers differ, your insurer’s version governs your bill.

FAQs About Psychiatrist vs Therapist

Can a therapist diagnose me? Licensed therapists can diagnose mental health conditions within their scope of practice. They cannot investigate medical causes, order bloodwork, or prescribe. Where a physical cause might be producing symptoms, a medical assessment is needed alongside. Do I need a referral to see a psychiatrist? Often not, though some insurance plans require one. Many psychiatric practices accept direct booking. Check with both the practice and your insurer, since a plan may require referral for coverage even where the practice does not require it for booking. Is a psychiatrist better than a therapist? Neither is better. They do different jobs. Psychiatrists handle medical assessment and medication. Therapists handle the structured work of changing thoughts, behavior, and patterns. Many people benefit most from both, coordinated with each other. Can my family doctor treat my depression? Primary care physicians manage many straightforward cases of depression and anxiety effectively. Specialist referral is worth considering where symptoms are severe, where two medications have not worked, where the diagnosis is unclear, or where a controlled substance such as an ADHD medication is involved. How long is the wait to see a psychiatrist? Waits vary considerably by area and practice, and are frequently longer than for therapy. If you expect to need both, booking the psychiatric assessment early when beginning therapy sooner is a practical approach rather than waiting for one before starting the other.

Book the Right First Appointment

If medication is likely part of the answer, or two treatments have already failed, a psychiatric assessment is the appointment that moves things forward. Dr. Sambunaris & Associates provides psychiatric care in Alpharetta, Georgia, serving Roswell, Johns Creek, Milton, and Sandy Springs. Book My Assessment or call (770) 817-9200. Reviewed by Angelo Sambunaris, M.D., with more than 20 years of clinical experience. If you are having thoughts of suicide or self-harm, call or text 988 to reach the Suicide and Crisis Lifeline, available 24 hours a day. This article is general information, not medical advice.  

PTSD in First Responders: The Hidden Career Cost

It is rarely one call. It is four hundred of them, and the one that finally will not leave.

Table of Contents

  1. How PTSD in First Responders Develops
  2. Cumulative Exposure and Moral Injury
  3. Why It Goes Unreported
  4. What Confidentiality Actually Means
  5. Signs Colleagues and Families Notice First
  6. Treatment That Fits the Job
  7. FAQs About PTSD in First Responders
You have been doing this for eleven years. You are good at it. You have stopped sleeping properly, you are drinking more than you used to, and last month a routine call put you somewhere you could not explain afterward. Nobody at work has noticed, since you are good at this too. PTSD in first responders and veterans develops differently from PTSD after a single civilian trauma. This guide covers how cumulative exposure works, why disclosure feels impossible, and what treatment can realistically look like alongside a career.

How PTSD in First Responders Develops

PTSD in first responders more often develops from repeated exposure to traumatic events across a career rather than from one incident. The cumulative pattern means there is frequently no single identifiable trauma to point to, which can make both recognition and disclosure harder. Occupational factors including shift work, sleep disruption, organizational stress, and the expectation of composure add to the burden alongside the exposures themselves. That absence of a single event matters practically. People expect PTSD to have a story attached. Cumulative trauma often does not, which leads to the assumption that what you are experiencing cannot be PTSD.

Cumulative Exposure and Moral Injury

Two mechanisms operate alongside each other. Cumulative exposure. Repeated traumatic events without adequate recovery between them. Each may be manageable individually. The accumulation is what produces the difficulty, often with a delayed onset years into a career. Moral injury. Distress arising from events that violate deeply held moral beliefs. Being unable to save someone. Following a protocol that produced a bad outcome. Witnessing something you could not prevent. Decisions made with incomplete information under time pressure. Moral injury is not the same as PTSD, and the two frequently occur together. Where PTSD is characterized by fear and threat, moral injury centers on guilt, shame, and a changed sense of yourself as a person. That distinction matters for treatment. Fear-based approaches address one mechanism. Guilt and shame require different work. Veterans and first responders both report both, and the overlap is substantial.

Why It Goes Unreported

The barriers here are specific rather than general reluctance. Career consequences. Genuine and widely believed concerns about fitness for duty assessments, restricted duties, or effects on promotion. Culture. Environments where composure under pressure is a core professional value, and where struggling can read as unsuitability. Weapons and licensing. For law enforcement and some veterans, concerns about firearm access following a mental health disclosure. Identity. The role is not just a job. Admitting difficulty can feel like admitting you can no longer be the person you have been. Not wanting to burden peers who are carrying the same exposures. These are not irrational. They are practical concerns about real systems, and dismissing them does not help. What is worth weighing against them is the alternative trajectory. Untreated symptoms tend to worsen, and the outcomes at that end, including relationship breakdown, substance use, and suicide risk, are considerably worse than a period of treatment.

What Confidentiality Actually Means

Uncertainty here keeps people out of treatment, so it is worth stating clearly. Treatment with a private practitioner is confidential. Your employer is not informed that you are attending, and clinical records are not shared with them without your written authorization. Limits exist and are narrow. They usually involve imminent risk of serious harm to yourself or others, suspected abuse of a child or vulnerable adult, and specific legal orders. These are explained at a first appointment. Where an employer-mandated evaluation is involved, that is a different arrangement with different reporting, and it should be made explicit at the outset which you are attending. Ask directly at your first contact. What is shared, with whom, and under what circumstances. Any practice should answer that plainly. Paying privately rather than through an employer-linked program is an option some people choose for this reason.

Signs Colleagues and Families Notice First

Families usually see it before employers do, and often before the person does. At home. Emotional distance, irritability disproportionate to the situation, unwillingness to discuss work, sleep disruption and nightmares, increased drinking, and withdrawal from things previously enjoyed. At work. Increased sick leave, avoidance of particular call types or locations, uncharacteristic errors, cynicism, and reduced tolerance for colleagues. In themselves. Hypervigilance that does not switch off at home, intrusive images arriving unbidden, feeling detached from people, and a sense of being permanently on. The at-home irritability is usually the first thing a partner raises, and it is frequently what eventually brings someone to an appointment. For families, naming what you have observed in particular works better than asking whether someone is alright. “You have not slept properly in two months and you are drinking most nights” is harder to deflect than a general question.

Treatment That Fits the Job

Several practical considerations shape what works for this group. Trauma-focused therapies including prolonged exposure, cognitive processing therapy, and EMDR have the strongest evidence, including in military and first responder populations. Cognitive processing therapy suits moral injury presentations particularly, since it addresses guilt and belief rather than only fear. Shift work complicates scheduling and sleep, both of which affect treatment. That is a practical problem to plan around rather than a barrier. Sleep and substance use frequently need addressing alongside. Alcohol used to manage symptoms is extremely common in this group and undermines treatment when it continues. Medication may be used alongside therapy, with the usual considerations. Peer support has value and does not replace clinical treatment. The National Center for PTSD publishes extensive resources for veterans and first responders, and veterans enrolled in VA care can access treatment through that system.

FAQs About PTSD in First Responders

Can PTSD develop without one specific traumatic event? Yes. Cumulative exposure across a career is the more common pattern in first responders and military personnel. The absence of a single identifiable incident does not rule out PTSD and is a recognized route to it. Onset is frequently delayed, appearing years into a career. Will treatment affect my job? Treatment with a private practitioner is confidential, and your employer is not informed you are attending. Records are not shared without your written authorization, with narrow exceptions involving imminent risk of serious harm. Employer-mandated evaluations are a separate arrangement with different reporting, which should be clarified upfront. What is moral injury? Distress arising from events that violate deeply held moral beliefs, such as being unable to prevent harm or following a protocol that produced a bad outcome. It centers on guilt and shame rather than fear, which is what distinguishes it from PTSD. The two frequently occur together and moral injury may need different therapeutic emphasis. How do I raise it with someone I work with? Name what you have observed in particular rather than asking usually whether they are alright. Sleep, drinking, and withdrawal are concrete and harder to deflect. Ask directly about suicide if you are concerned, since asking does not increase risk. Offer something specific rather than telling them to get help. Is it too late if this started years ago? No. Trauma-focused treatment is effective regardless of how long ago the events occurred, including decades later. Many people first seek treatment years afterward, often when something triggers a return of symptoms or when a relationship reaches a crisis point.

Book a Confidential Assessment

An assessment is confidential, your employer is not informed, and nothing is decided at a first appointment beyond what is going on. Dr. Sambunaris & Associates treats PTSD in Alpharetta, Georgia. Book My Assessment or call (770) 817-9200. Reviewed by Angelo Sambunaris, M.D., with more than 20 years of clinical experience. If you are having thoughts of suicide or self-harm, call or text 988 to reach the Suicide and Crisis Lifeline, available 24 hours a day. Veterans can press 1 to reach the Veterans Crisis Line. This article is general information, not medical advice.  
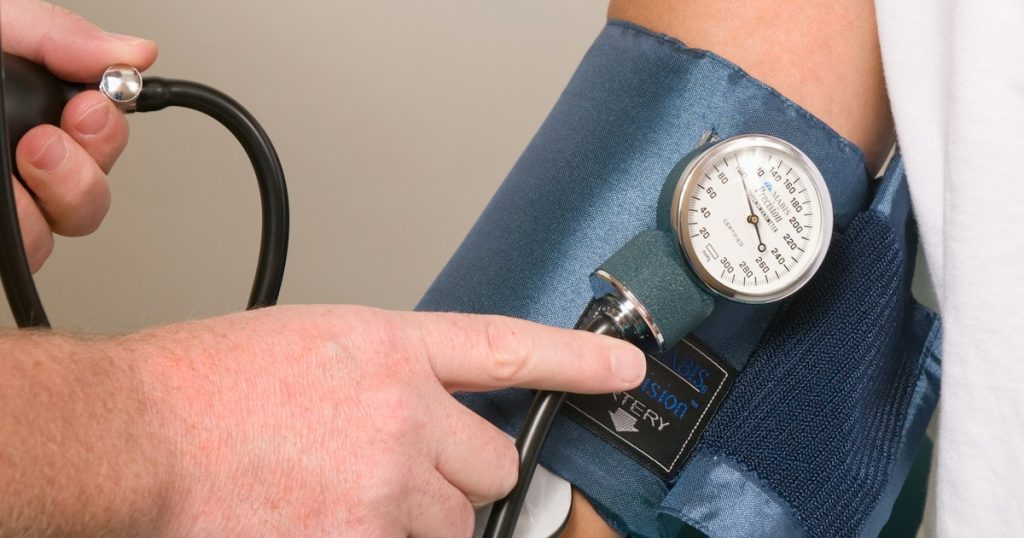
Clinician checking a patient's blood pressure with an arm cuff and gauge

IM Ketamine Side Effects: Who Should Avoid It

Most side effects show up during the visit and ease as the drug wears off. The serious risks are the reason screening comes first.

Table of Contents

  1. Is IM Ketamine Safe? The Short Answer
  2. Side Effects During a Session
  3. The Blood Pressure Question
  4. What Dissociation Feels Like
  5. Who Should Avoid Ketamine
  6. Risks That Come With Repeated Use
  7. Medications and Interactions
  8. Why the Setting Matters
  9. FAQs About IM Ketamine Side Effects

People considering ketamine usually arrive with two worries. One is what it will feel like. The other is whether it is dangerous.

Both deserve straight answers. Ketamine has real side effects and a few serious risks, and it is not suitable for everyone. In a monitored medical setting, with proper screening beforehand, most of what happens during a session is short-lived and manageable.

Is IM Ketamine Safe? The Short Answer

For carefully selected patients treated in a supervised setting, the published safety record for intramuscular (IM) ketamine is reassuring.

One large real-world report followed patients at US outpatient clinics over 2,532 IM treatments (Ahuja et al., BMC Psychiatry, 2022). An adverse event occurred in 2.3% of treatments. Nausea was the most common at 1.9%, and no severe adverse events were observed. Abnormal vital signs appeared in 0.16% of treatments, and all stabilized within 30 minutes.

That study had no control group, and its patients had already been screened. Its numbers describe what happens when the right people are treated the right way. They are not a promise for everyone.

Side Effects During a Session

The FDA label for Spravato, the esketamine nasal spray, gives the most detailed list from controlled trials. Its most common adverse reactions in treatment-resistant depression included:

  • Dissociation
  • Dizziness and vertigo
  • Nausea and vomiting
  • Sedation and lethargy
  • Reduced sensation, or numbness
  • Anxiety
  • Increased blood pressure
  • Headache
  • Feeling drunk

Esketamine and standard ketamine are closely related, so the same effects are expected with IM ketamine, though the rates may differ.

Most of these show up during the session and ease as the drug wears off. That timing is why monitoring happens on site rather than at home.

The Blood Pressure Question

Ketamine raises blood pressure for a while. This is the side effect with the most bearing on who can be treated.

The American Psychiatric Association consensus statement describes one study of 84 patients receiving IV ketamine for depression. Blood pressure rose on average by about 20 points systolic and 13 points diastolic during treatment. Around 30% of patients briefly passed 180/100 or a heart rate of 110 at some point. There were no lasting medical complications.

For esketamine, the label says blood pressure rises peak about 40 minutes after dosing and last about 4 hours.

That is manageable in a healthy person. It is a different matter for someone whose blood vessels cannot safely take the strain. The ketamine prescribing information lists it as contraindicated in patients for whom a significant rise in blood pressure would be a serious hazard. This is why blood pressure is checked before every session and watched during it.

What Dissociation Feels Like

Dissociation is the effect people ask about most.

The FDA describes it as a disconnection between a person’s thoughts, feelings, and sense of space, time, and self. People often describe feeling detached, dreamlike, or as if watching from a distance. Some find it pleasant. Some find it unsettling, especially the first time.

The APA consensus statement calls these effects transient, and advises that the treating clinician be prepared to manage marked changes in mental state if they occur.

Clinics often keep the room quiet and dim, and the Ahuja clinics also used eye shades and calm music. The ketamine label advises keeping verbal, touch and visual stimulation low to ease reactions during recovery. It also helps to know in advance that the feeling is expected and that it ends.

Who Should Avoid Ketamine

Screening exists because a small number of conditions change the balance of risk entirely.

Conditions where a blood pressure spike is dangerous. The ketamine label names this as a contraindication. The Spravato label lists specific examples: aneurysmal vascular disease, arteriovenous malformation and a history of bleeding in the brain.

Allergy to ketamine. Known hypersensitivity to ketamine is a contraindication on both labels.

A history of psychosis. The APA consensus statement recommends that the evaluation check for psychotic disorders, and notes that the strongest evidence is in depression without psychotic features.

Current or past substance misuse. Ketamine has known abuse potential, so the evaluation asks about substance use in detail. The consensus statement encourages confirming that history with family members where possible.

Pregnancy. The Spravato label warns esketamine may cause fetal harm and advises pregnancy planning and prevention for women who could become pregnant.

Uncontrolled high blood pressure also needs attention before treatment. The Spravato label advises weighing the risk carefully when baseline blood pressure is elevated, for example above 140/90.

None of this is a do-it-yourself checklist. It is what your psychiatrist works through at the evaluation.

Risks That Come With Repeated Use

Some risks relate less to a single session and more to how often ketamine is used over time.

Bladder and urinary problems. Serious urinary complications, including cystitis, have been reported with long-term ketamine use or abuse, according to the ketamine label. In Spravato clinical studies lasting up to a year, no cases of esketamine-related interstitial cystitis were seen, though urinary symptoms were more frequent than with placebo.

Liver effects. In March 2026 the ketamine label added a warning about liver and bile duct problems with recurrent use, including medically supervised use for unapproved indications. It recommends baseline liver function tests for patients on a plan that involves repeated dosing.

Memory and thinking. The APA consensus statement links chronic, high-frequency ketamine use with possible cognitive impairment.

Misuse. The consensus statement asks clinicians to stay alert to the potential for ketamine use disorder.

The consensus statement recommends checking cognition, urinary symptoms and substance use during a course of repeated treatments. Ask your clinician how they monitor each one.

Medications and Interactions

Tell your psychiatrist about everything you take, including supplements and alcohol.

The ketamine label warns that combining it with benzodiazepines, opioid pain medication, alcohol or other sedating drugs may cause profound sedation and slowed breathing. The Spravato label adds psychostimulants, such as amphetamine and methylphenidate ADHD medications, and MAO inhibitors, both of which may push blood pressure higher.

That does not always rule treatment out. It can change the timing or the plan. Do not stop or adjust any prescription on your own to qualify for ketamine. Your psychiatrist will tell you what, if anything, needs to change.

Why the Setting Matters

The same drug carries different risks depending on where it is taken.

In October 2023 the FDA issued a compounding risk alert about compounded ketamine products sold for at-home use. It warned that using them without a health care provider monitoring for sedation, dissociation and changes in vital signs may put patients at risk of serious adverse events.

A supervised IM session addresses exactly that. Vital signs are measured before the dose, a clinician is present while the effects peak, and you leave only when you are steady. At our practice, treatment starts with a physical exam and a review of your medical history.

FAQs About IM Ketamine Side Effects

Is IM ketamine addictive? Ketamine has recognized abuse potential. In a supervised medical course, doses are measured, given only in the clinic, and paired with screening for substance use history. The APA consensus statement recommends ongoing vigilance for signs of misuse during treatment.

Will I hallucinate? Perception often changes during a session, and some people experience vivid imagery. These effects are usually temporary and pass as the drug wears off. Your clinician is there throughout.

Can I drive myself home? No. For esketamine, the FDA label says not to drive or operate machinery until the next day after a restful sleep. The same caution is sensible after IM ketamine, so arrange a ride in advance.

I have high blood pressure. Can I still have ketamine? Possibly. Well-controlled blood pressure does not automatically rule you out, but it needs assessing first. Talk to your psychiatrist, who will weigh your readings and heart health before recommending treatment.

How do side effects of IM compare with IV or Spravato? The types of effects are broadly similar across all three. Our comparison of IM ketamine, IV infusion and Spravato covers how the routes differ in dosing, monitoring and cost.

Start With an Evaluation

Whether ketamine is safe for you depends on a full picture of your health. That is what the first appointment is for. If you want to know what treatment itself looks like, read what an IM ketamine session involves.

Dr. Sambunaris & Associates provides ketamine therapy in Alpharetta, Georgia, including for PTSD.

Book My Evaluation or call (770) 817-9200.

Reviewed by Angelo Sambunaris, M.D., with more than 20 years of clinical experience and over 30 years in clinical research.

If you are having thoughts of suicide or self-harm, call or text 988 to reach the Suicide and Crisis Lifeline, available 24 hours a day.

Medical Disclaimer: This article is for general educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Ketamine is not FDA approved for the treatment of depression or any other psychiatric disorder, and its use for these conditions is off-label. Reading this article does not create a doctor-patient relationship. Always talk to your doctor or another qualified health provider about your own situation, and never start, stop, or change medication without speaking to your prescriber. If you think you may be having a medical emergency, call 911.